Lupine Publishers | Journal of Otolaryngology

Necrotizing periodontal diseases are the most severe rapidly
destructive, non-communicable, periodontal infection of complex
etiology. The diagnosis is based on clinical and radiological features.
Necrotizing periodontal lesions are confined to periodontal
tissues, including gingiva, periodontal ligament, and alveolar bone. The
pathognomonic clinical characteristics are the typical
punched out appearance, interproximal craters and spontaneous bleeding.
The predisposing factors include host factors, such as
psychological stress, immunosuppression, a smoking habit, and poor oral
hygiene. If it is left untreated, it may spread laterally
and apically to involve the entire gingival complex. In this case
report, we presented a 24- year old male with necrotizing gingivitis
and no systemic disease with a history of intense stress. The case
report describes the clinical diagnosis of Necrotizing ulcerative
periodontitis (NUP) and its therapeutic management by conservative oral
treatment and regular psychological follow up.
Keywords: Necrotizing periodontal disease; Diagnosis; Treatment
Abbreviations: NUP: Necrotizing ulcerative periodontitis; NPD: Necrotizing periodontal diseases; NP: Necrotizing Periodontitis
Introduction
Necrotizing periodontal diseases (NPD) are the most severe
inflammatory periodontal disorders associated with bacterial
plaque. It usually has a rapid, aggressive onset, a multifactorial,
complex etiology and runs an acute course [1]. They are classified
as necrotizing gingivitis, periodontitis, or stomatitis according
to the severity of progression of disease and tissue involvement
[2]. Classical clinical features in necrotizing periodontitis (NP)
are characterized by the presence of punched out, ulcerated and
necrotic lesions that may be covered by a pseudo membrane of
necrotic tissue [3]. The ulcerations are extremely painful and show
spontaneous bleeding. An important feature of NP is the rapid and
severe loss of clinical attachment and alveolar bone within a few
days or weeks. Secondary clinical features include the presence
of fever, oral halitosis, adenopathies and/or general discomfort
[3]. This form of gingivitis is relatively rare. A heterogenous
set of proliferating oral anaerobic bacteria such as spirochetes,
fusobacteria, and strains of Treponema pallidum and Bacteroides
intermedius are involved in the development of the clinical signs
and symptoms of the disease.1 Primary risk factors for disease
include smoking, psychological stress, poor nutrition. Defects
in leukocytes and immune function may also be associated with
disease occurrence [2]. Here, we report a case of a necrotizing
ulcerative gingivitis in a 24 year old male, describing the clinical
features, treatment approach, and successful outcomes.
Case Report
Patient information
A 24-year-old male patient was referred to the Clinical
Department of Periodontology, at the Krishnadevaraya College
of dental sciences and hospital Bangalore, with chief complaint
of intense and persistent gingival pain, bleeding and foul breath
since a year which aggravated in the past two weeks. He weighed
60 kg and was 182 cm tall and is a dance artist by profession. The
patient gives a history of intense stress for the past few months,
improper intake of nutrition and intense stress. The patient also
reports elevated body temperature since the past two days and no history
of drug allergies, current medications, or significant health
problems. Presence or absence of Vincent’s angina symptoms is
mentioned in Table 1. Also, Table 2 shows predisposing factors of
the disease.
Table 1: Symptoms of Disease in the Patient.
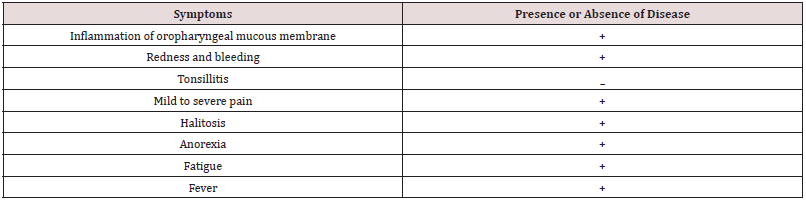
+: positive, - : negative.
Table 2: Evaluation of Predisposing Factors in Index Case.
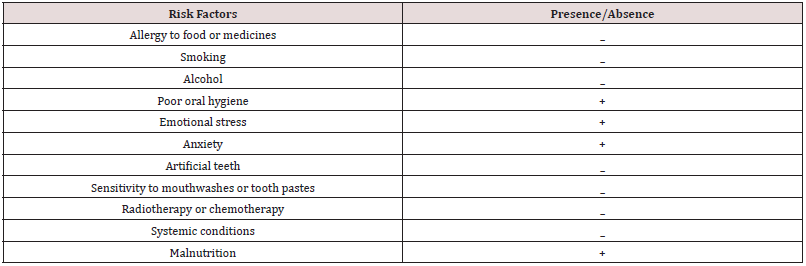
+: positive, - : negative.
Clinical and Diagnostic Findings
Extra-oral examination
On extra oral examination, there was no gross facial asymmetry
detected, lips were competent, bilateral submandibular lymph
nodes were tender on palpation and local rise in body temperature
was detected.
Intra-oral examination
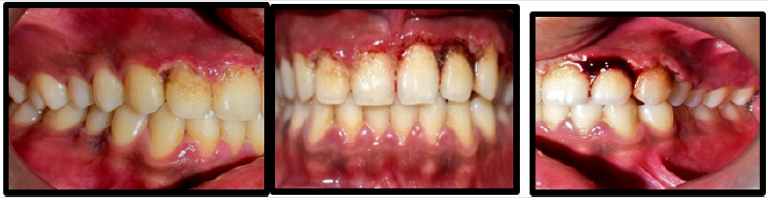
Clinical findings: On intraoral examination, poor oral hygiene
was recorded with plaque, heavy calculus deposits, visible
suppuration associated with fetor oris. The oral lesions were
extremely tender hindering periodontal probing. Examination of
the gingiva revealed a thin pseudo-membrane that covered a part
of the attached gingiva with spontaneous bleeding or on slight
provocation. The typical multiple punched out like depressions
were found more in interdental papilla and marginal gingiva. The
ulcers were found to be more severe and painful in maxilla. The
patient had an aberrant labial frenum in the maxilla which added to
the severity of lesion in maxillary anterior teeth (Figure 1).
Figure 1: Baseline photograph showing the necrotizing lesion and aberrant frenum.
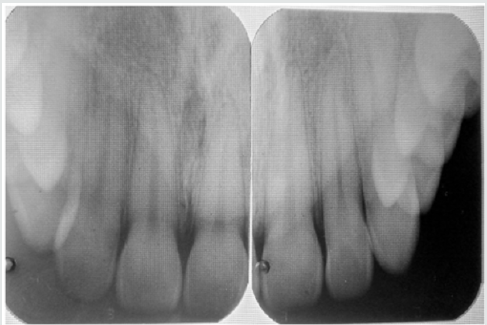
Radiographic findings: A periapical radiographic examination showed crestal alveolar bone loss in the affected area (Figure 2).
Figure 2: Radiograph showing minimal alveolar bone loss.
Therapeutic Interventions
First Visit:
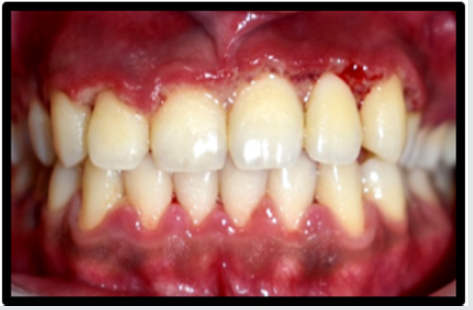
In the first visit conservative treatment like removal of local
factors and maintenance of oral hygiene was done (Figure 3).
Removal of the necrotic slough was done under local anaesthesia
by using small gauze pellets dipped in 3% H2O2. This procedure was
done in all the affected areas of the mouth and then the areas were
irrigated with saline to remove the unattached debris. Supragingival
scaling couldn’t be done with ultrasonic scaler as the patient was
having discomfort. He was instructed to use a soft brush, hydrogen
peroxide 3% mouth rinse with sterile warm water (1:1) four times
a day and chlorhexidine 0.2% mouthwash twice daily. The patient
was prescribed amoxicillin and metronidazole 500 mg tablets
three times per day for 5 days, an analgesic, vitamin complexes and
a follow up appointment was scheduled. The Patient was recalled
after 3 days for evaluation.
Figure 3: Post scaling and irrigation.
Third visit:
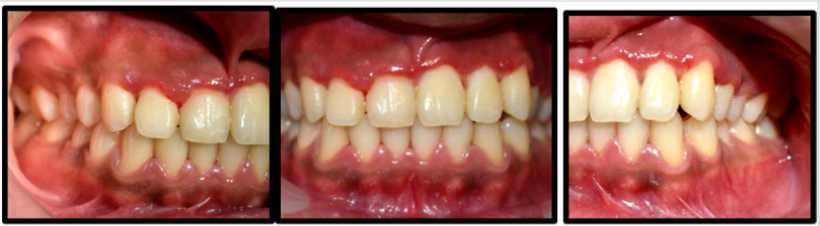
On the third day of the recall visit a drastic improvement was
observed. The ulcers were showing signs of healing, no bleeding
points were detected, pain had reduced, and necrotic slough had
decreased considerably. The ulcers were still found in the tip of
the interdental papilla, inflammatory enlargement was observed
(Figure 4). Lymph nodes were palpable but non tender and the
temperature was also normal. Complete scaling was done including
subgingival areas to remove local deposits and the ulcerated sites
were irrigated with saline. He was instructed to discontinue the
hydrogen peroxide mouth rinse and continue the chlorhexidine
mouthwash till the next visit which was planned after 4 days.
Figure 4: Third day follow up showing moderate inflammation which is resolving..
At Seventh day
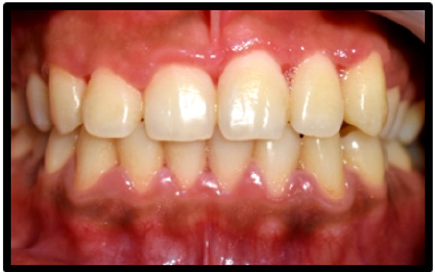
After seven days the patient was almost symptom free. The
ulcers had healed and necrotic slough was completely absent. Slight
inflammatory enlargement was seen in the maxillary anterior labial
and tip of interdental papilla (Figure 5). Oral hygiene instructions
were reinforced with prescription of interdental brushes and
dental floss to perform mechanical plaque control. Additionally, he
was advised to use Chlorhexidine mouth rinse 0.12% twice a day
for further 10 days. Patient was referred to a psychologist to rule
out his stress due to his profession. Patient was advised to maintain
oral health by regular dental visits and strict oral hygiene practice.
Figure 5: One week follow up showing minimal residual inflammation.
Maintenance phase
After the completion of the cause-related therapy phase,
the patient was enrolled in a periodontal maintenance program
to optimize the therapeutic interventions which was done by
the patient’s adherence to the recall system of weekly followup
appointments. Monthly follow-up for the first 3 months post
treatment were done and at each visit, the oral hygiene instructions
were emphasized.
Clinical outcomes
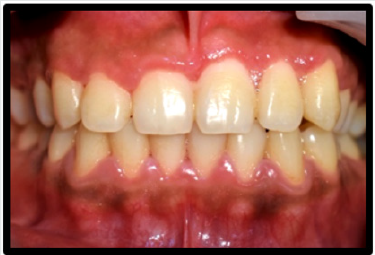
Figure 6: Three months follow up showing completely healed lesion.
The patient was very compliant and responsive to the
treatment provided. At three month recall visit, there was a
complete resolution of inflammation and a healing of ulcerated
areas with epithelialization of gingival interdental craters (Figure
6). A psychologist was consulted, and the patient was kept on
maintenance with instructions of oral hygiene and proper nutrition.
The findings at multiple follow-up examinations showed that
periodontal health and function were successfully re-established
and there was no evidence of progressive attachment loss (Figure
6).
Discussion
Necrotizing periodontitis (NP) is a necrotizing periodontal
disease that has an acute onset and requires urgent treatment [1].
The pathognomonic clinical characteristics are the typical punched
out appearance and interproximal craters which were evident
in our patient. Although its clinical signs are characteristic, the
etiology and pathogenesis is still not clear. It is a known fact that
the pathogenic processes involved in any periodontal diseases is
initiated by bacterial plaque and modified by predisposing factors
[2-4]. The bacterial species like fusiform bacilli and spirochetes are
dominated in necrotizing periodontal diseases. However, it is not
clearly established whether this flora is the cause because of their
capacity to invade the epithelium and the connective tissue where
they release endotoxins or the consequence of the disease and then
they may result from a secondary growth since the necrotic tissues
are the perfect environment for bacterial colonization and tissue
invasion [5]. Predisposing systemic factors such as AIDS, diabetes,
chemotherapy or leukemia are described in the literature to be
associated with most cases of NUP [6-8]. In our patient a systemic
disease was ruled out since biological analysis was normal and he
was otherwise healthy.
This case report describes an acute presentation of necrotizing
gingivitis associated with poor oral hygiene, malnutrition, and
lack of sleep which are all related to intense psychological stress.
Many pathways have been suggested to explain study evaluated the
association between levels of the stress-related steroid hormones
and periodontitis and reported that high serum levels of cortisol
were associated with periodontitis severity [9]. Host immune
response to periodontal pathogens may be reduced by increasing
the adrenocortical activity, which lead to altered cytokine profile
and affected cells recruitment of macrophages and fibroblasts [10].
Stress also causes reduction of tissue matrix metalloproteinase
levels, which leads to impaired tissue turnover. During stress
periods, the subject’s behavior also change and can lead patients to
neglect oral hygiene. Malnutrition related to extreme stress has also
been reported as a predisposing factor for necrotizing periodontal
diseases. The basis for this interaction has been termed ‘proteinenergy
malnutrition’, implying a marked reduction in antioxidant
nutrients and an altered acute-phase response against infection
[5]. The management strategy for NP lesions were followed in two
phases: acute and maintenance phase treatment. The acute phase
dealt with removal of local irritating factors. The patient’s positive
response to the intervention within one week could be attributed
to several factors: use of systemic antibiotics like metronidazole,
which has been described as the first antibiotic choice because it is
active against strict anaerobes, proper oral hygiene, use of vitamin
complexes and adequate rest.
Conclusion
Necrotizing ulcerative lesions, although uncommon, can cause
severe pain and discomfort to the patient. It is always associated
with underlying systemic illness and hence thorough history
recording and clinical examination becomes the key to successful
diagnosis and treatment.
Read More Lupine Publishers Otolaryngology
Journal
Articles:
https://lupine-publishers-otolaryngology.blogspot.com/